Home health lives in a different world than non-medical home care: your biggest referral source often wears a badge, not a search bar, a discharge planner, a case manager, a physician's office. But the family still googles you before they say yes. We build marketing that works both angles at once, because senior-serving brands are the only clients we take.
A referral source needs to trust your clinical capability in seconds. A family needs to feel safe letting a clinician into their parent's home. Home health marketing has to hold both truths on the same site without diluting either one.
Medicare-certified agencies where compliance language has to be accurate, not just persuasive
Referral relationships with hospitals, physicians, and discharge planners that a website should reinforce, not replace
Families vetting clinical credentials, licensure, and staff qualifications before they'll say yes to in-home visits
A crowded local market where 'home health' and 'home care' get confused by searchers and search engines alike
Two audiences, one strategy.
Home Health SEO
Clear separation from "home care" in your site's language and structure, backed by local SEO and Google Business Profile management, so you rank for the clinical searches, not just the non-medical ones.
Home Health Digital Marketing
Referral-source content and materials built to make discharge planners and physicians comfortable referring you fast, paired with compliant, trust-building copy for the family googling you afterward.
Home Health Lead Generation
A pipeline that works both referral and direct-search channels at once, with full-funnel follow-up so a physician referral or a family inquiry gets the same fast response.
Home Health Website Design
Messaging that respects Medicare and state licensing rules while still answering the questions a nervous family is actually asking. See our home health website design work.
Families cannot tell you apart from home care, and the data proves it
Home health and home care are different businesses with different clinicians, different regulation and, most importantly, different payers. To a family three days after a hip replacement they are two phrases that sound identical.
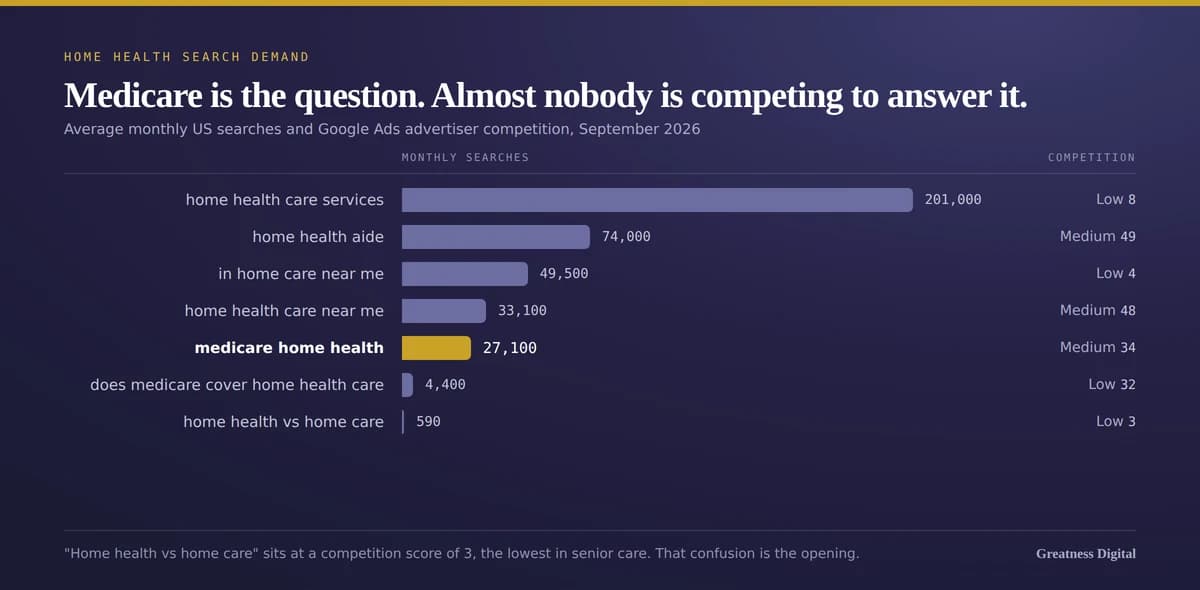
Competition score 3On “home health vs home care.” The lowest number we have found anywhere in senior care, on the exact question families are stuck on.
Almost nobody is bidding to answer it, and almost nobody has written the plain-English version. That is a small-volume term, around 590 searches a month, but it is the doorway question. A family who understands the distinction because your page explained it has already started trusting you, and they now know which of the two they actually need.
We can be blunt about why this matters, because we watched it happen on our own site. For a week this page outranked our dedicated memory care and assisted living pages for their own terms, purely because it was thin enough that Google could not tell what it was about. If a page with 400 words can drift that far off topic, so can yours.
Google Ads keyword data, September 2026. The lowest competition score in the whole category sits on the question families are most confused by.
Medicare is your differentiator, and it is the opposite answer from assisted living
This is the most valuable thing you can say, and most agency websites bury it in a paragraph about compassionate clinicians.
~31,000 a monthUS searches across “medicare home health” and “does medicare cover home health care,” at low to medium competition and a cost per click near $4 on the question form.
For assisted living the honest answer to the Medicare question is no, and saying so is a trust play. For home health the answer is frequently yes, when a physician certifies the need, the care is intermittent, and the agency is Medicare-certified. That is a materially different conversation, and it is the single strongest reason a family should call you rather than a private-pay alternative.
Write it plainly. The certification you hold, the criteria in normal words, what the family will and will not be billed for. These are extractable, factual claims, which means an AI assistant can repeat them when somebody asks what Medicare covers in your county. “We accept Medicare” is not enough to repeat.
The biggest term in your category is the wrong intent
“Home health aide” draws about 74,000 US searches a month. It looks like the prize. It is mostly people looking for a job.
Chasing it with a service page wastes the traffic, and worse, it teaches search engines that your site answers an employment query. Then the page that should be pulling families pulls applicants instead.
Which is not a reason to ignore it. Staffing is the constraint on how many referrals a home health agency can actually accept, so that demand is worth something real, just not on the page you are using for census. Give recruiting its own page and its own tracking. Then the numbers stop lying to you about which half of the business is working.
Your referrals are offline. Your verification is not.
Home health census is largely referral-driven, and that leads a lot of agencies to conclude that digital marketing is beside the point. The conclusion is wrong, but the premise is right.
A discharge planner names three agencies. The family looks up all three before they call one. A hospital liaison who recommends you is putting their own credibility on the line against whatever that family finds in the next ninety seconds.
So the job is not lead generation in the usual sense. It is making sure the verification step goes well: star rating and Medicare certification visible, service area unambiguous, specialties named specifically, and the same details saying the same thing on your Google Business Profile and every directory that lists you. An inconsistent address or a stale phone number is not a cosmetic problem here. It is the moment a referral quietly goes to somebody else.
Authority is not the barrier you think it is
Agencies often assume a national chain with a bigger, older, more linked-to website will always take the local search. In hyper-local senior care the data says otherwise.
DR 55 loses to DR 2In a live Portland audit, a national chain with a Domain Rating of 55 ranked behind single-location competitors with Domain Ratings under 2.
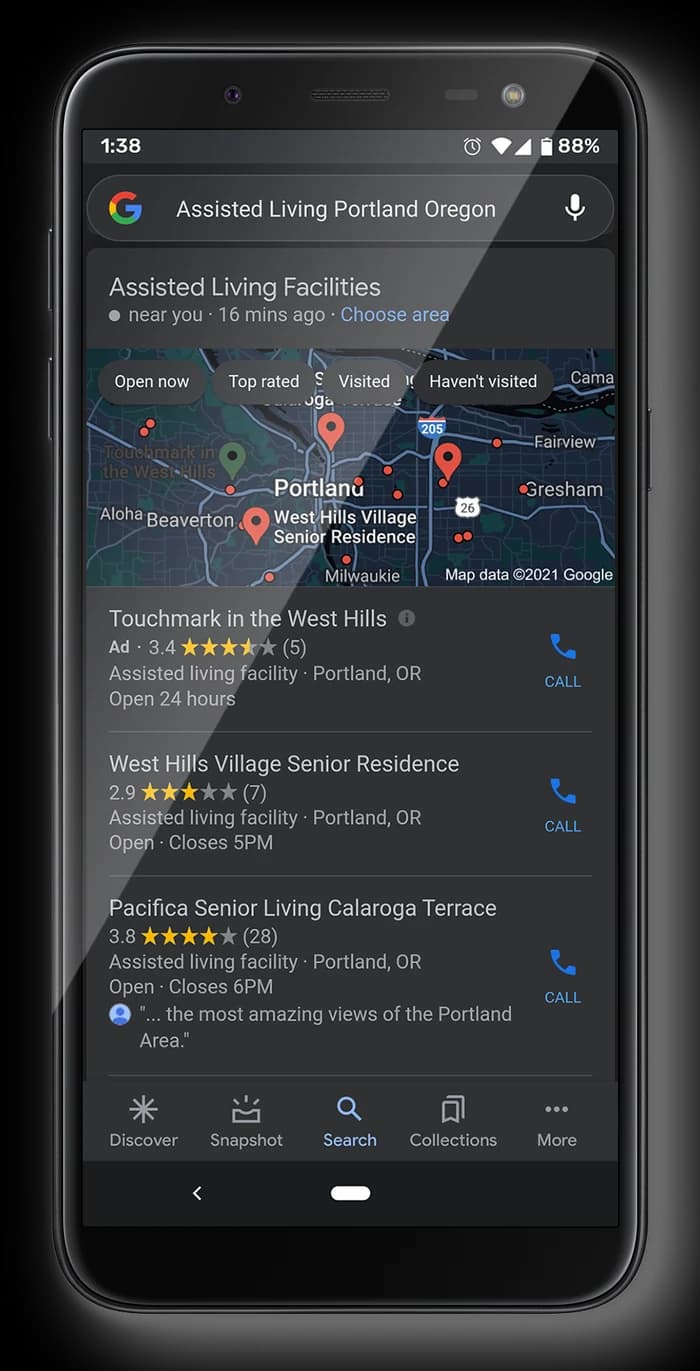
Google Business Profile strength and genuine on-page local relevance separated them, not backlink authority. Since “home health care near me” is a proximity query, the Local Pack sits above every organic result, and it is won with citation consistency and a profile somebody actually maintains.
A live local senior care search. The Local Pack takes the whole first screen, before a single organic result.
What we measure, and what we will tell you
Cost per admission is the number that matters, and we track cost per lead alongside it, because the gap between the two is where the diagnosis lives. A healthy cost per lead paired with a bad cost per admission is a funnel problem, not a budget problem.
We also track AI mention rate monthly, firing real buying-intent prompts across ChatGPT and Perplexity and recording how often the brand gets named.
And we will tell you when a number is not real. We came close to sending a client a report showing four months of decline that had not happened, because one data source was reporting against a stale canonical record while three others disagreed. That story is written up here, including the part where we were confidently wrong.
What is the difference between home health and home care?
Home health is clinical and prescribed: skilled nursing, physical or occupational therapy, wound care, delivered under a physician’s plan of care and usually time-limited. Home care is non-medical support with daily living, such as bathing, meals, companionship and transport, and it can continue indefinitely. The payer differs too, which is the part that matters most to families. Medicare frequently covers home health when the criteria are met. It does not cover non-medical home care.
Does Medicare cover home health care?
Often yes, which makes it the opposite answer from assisted living. Medicare covers intermittent skilled nursing or therapy at home when a physician certifies the need, the care is intermittent rather than around the clock, and the agency is Medicare-certified. Homebound status is generally required. About 31,000 US searches a month hit some version of this question, and answering it plainly on your own site is the single cheapest piece of trust a home health agency can buy.
What keywords should a home health agency target?
The clinical and payer terms, not the generic care terms. “Home health care services” draws around 201,000 US searches a month at a competition score of 8, and the Medicare cluster adds roughly 31,000 more at similarly low competition. Avoid building your census strategy around “home health aide,” which carries about 74,000 searches a month but is mostly people looking for a job rather than families looking for care.
Is “home health aide” worth targeting?
Yes, but for recruiting rather than for census, and the two need separate pages. It is one of the larger terms in the category at roughly 74,000 US searches a month, and the intent behind most of it is employment. Pointing that traffic at a service page wastes it. Pointing it at a careers page addresses the staffing constraint that limits how many referrals an agency can actually accept.
How do home health agencies get referrals from discharge planners?
Referral relationships are built offline, but they are increasingly checked online. A discharge planner who has never heard of you will look you up, and a hospital liaison who recommends you is trusting their own reputation to what a family finds next. Your star rating, your Medicare certification, your service area and your specialties need to be immediately visible and consistent everywhere, because that is the verification step that happens after the conversation.
Should home health and home care share a website?
Only if each service has its own clearly separated pages. Many agencies offer both, and the temptation is to blend them because the operational overlap is real. The search intent is not blended. One family is asking what Medicare will pay for after a hospital stay, the other is asking who can help Mum shower on Tuesdays. A combined page hedges for both and answers neither, and it is the most common reason we see an agency rank for the wrong half of its own business.