The search no one wants to make. Answer it with dignity.
Nobody searches for hospice casually. By the time a family finds you, they're exhausted, grieving in advance, and deciding who spends time with someone they love in the time that's left. Marketing here has exactly one job: be findable and trustworthy without ever feeling like marketing. We take that seriously because senior-serving brands are the only clients we take.
Referral timing matters more here than almost anywhere else in senior care. A physician's referral, a hospital discharge, a family's own search, all have to lead somewhere calm, clear, and immediately reassuring, not a wall of clinical jargon or a hard sell.
Hospice and palliative providers where physician and hospital referrals are the backbone, and the website has to support that relationship, not compete with it
Families making a decision in acute grief, who need clarity and warmth, not persuasion tactics
Medicare hospice benefit questions that come up immediately and need a straight, accurate answer
A brand that has to feel present and human, because this is the opposite of a category where 'aggressive marketing' works
Findable. Never pushy.
Hospice SEO
Built with local SEO to show up when a family or a discharge planner searches for hospice care nearby, right when the decision is happening.
Hospice Digital Marketing
Compassion-first content that answers real questions (what does hospice cost, what does a nurse visit look like) without reading like a pitch, plus AI visibility so answer engines can cite you accurately and respectfully.
Hospice Referral & Lead Generation
Clear, professional pages built for the physicians and referral partners who need to trust you before they'll send a patient your way, alongside a direct-family inquiry path that never feels like a sales funnel.
The largest door in the category is the one most hospices treat as a footnote
On most hospice websites palliative care gets a sentence, sometimes a bullet. It is the bigger business by a wide margin, and it is the one families can accept before they are ready to accept anything else.
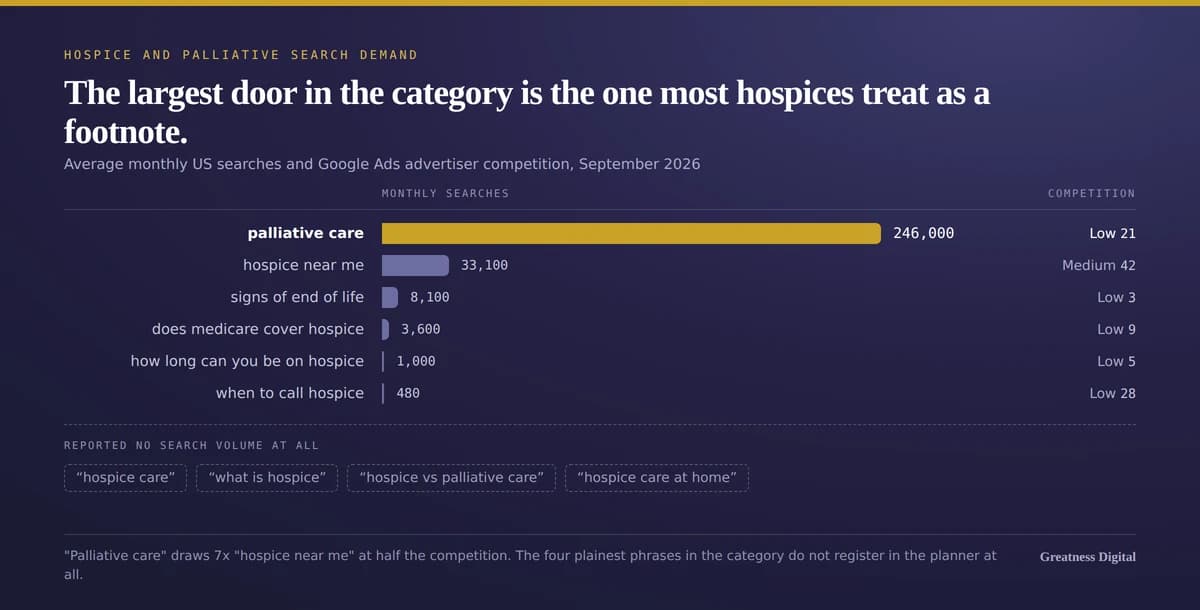
246,000 against 33,100Monthly US searches for “palliative care” against “hospice near me,” at advertiser competition scores of 21 and 42. Seven times the volume at half the competition.
The reason is not mysterious. Palliative care does not ask a family to give anything up. It runs alongside treatment, it is available years earlier, and the word does not carry what the word hospice carries. A family who is not ready to say the second word will readily search the first.
Which makes palliative the front door to the same organisation, and giving it one sentence means most of the people looking for you never arrive. It deserves its own page, its own explanation of what it is and is not, and an honest account of when it becomes hospice and what changes at that point.
Google Ads keyword data, September 2026. The four terms in the lower block returned no measurable volume, which is a fact about the tool as much as about demand.
The search that actually happens first is about symptoms, not services
Before anybody searches for a provider, they search to understand what they are looking at. That search is bigger than every provider term in the category except the two above it, and almost nobody is competing for it.
8,100 a month, competition 3On “signs of end of life.” Nearly seventeen times the volume of “when to call hospice,” at almost no advertiser competition.
It is worth being plain about who that is. Somebody awake at three in the morning, watching breathing change, trying to work out whether what they are seeing means what they think it means, and not wanting to wake anyone to ask.
That page has to be written as care and not as marketing, and the difference shows immediately. It means describing what happens clinically, in plain words, without a form in the middle of it and without urgency language anywhere near it. One quiet line at the end saying who to call and that it is not too late to ask. If the page reads as an attempt to convert somebody in that moment, it will fail, and it will deserve to.
We would rather say that out loud than write you a page that performs well and behaves badly. It is also, as it happens, what ranks: this is exactly the kind of genuinely useful, factual page an AI assistant will draw on when somebody asks it the same question at the same hour.
The plainest words in the category do not register at all
Everything above came from a keyword planner, so here is where that planner goes blind, and in this category it goes blind in a way that matters.
No volume reportedFor “hospice care,” “what is hospice,” “hospice vs palliative care” and “hospice care at home.”
“What is hospice” is not an obscure phrase. It is the first thing a person types when a doctor has just used the word. The planner reports nothing because it measures terms that reach the advertising auction, and a great deal of real human searching never gets there.
We have now hit this in three verticals running. The formal name of the whole medical equipment category reports no volume, and on senior move management five of the plainest family phrasings reported nothing while the trade term drew a fraction of the jobs inside it. Meanwhile Search Console on our own site shows a thirty-word conversational query ranking first.
The practical conclusion for a hospice is freeing. Write the explainer pages anyway. Write them for the sentence a person actually says, not the phrase a tool can price. The tool being unable to see that demand is not evidence that it is absent.
The most generous benefit in senior care, and the most misunderstood
We have written the payer question across seven verticals now, and this is the one where the answer is unambiguously good news and is still routinely not explained.
The Medicare hospice benefit covers the care team, the medications related to the terminal diagnosis, equipment, supplies and short inpatient respite, typically at little or no cost to the family. Set that against assisted living, where the honest Medicare answer is no, and it is the widest gap between two adjacent services anywhere in this sector.
Competition 5 and 9On “how long can you be on hospice” and “does medicare cover hospice,” about 4,600 US searches a month between them, almost uncontested.
The six-month figure is the piece most worth correcting. It is a certification standard, not a cap: a physician certifies a prognosis of six months or less if the illness runs its expected course, and patients can be recertified beyond that, or improve and leave hospice. Widely read as a deadline, it makes families wait, and waiting is how a benefit designed for months gets used for days.
Correcting that on your own site is one of the rare cases where the commercially useful thing and the clinically right thing are the same thing.
A correction we owe this page
We can be specific about why thin pages cause problems, because this page was the problem on our own site.
In our first month of Search Console data, this hospice page was answering memory care queries. It sat at position 23 for “memory care marketing agency” while our actual memory care page drew nothing. It was not a better answer. It was 500 words of its own copy surrounded by the same navigation and footer as every other page, so there was little to tell Google what it was about, and it drifted.
We have written that up honestly on the home health page too, which inherited the same role later. This rebuild is the fix for both: enough of its own substance that the page is unmistakably about one thing.
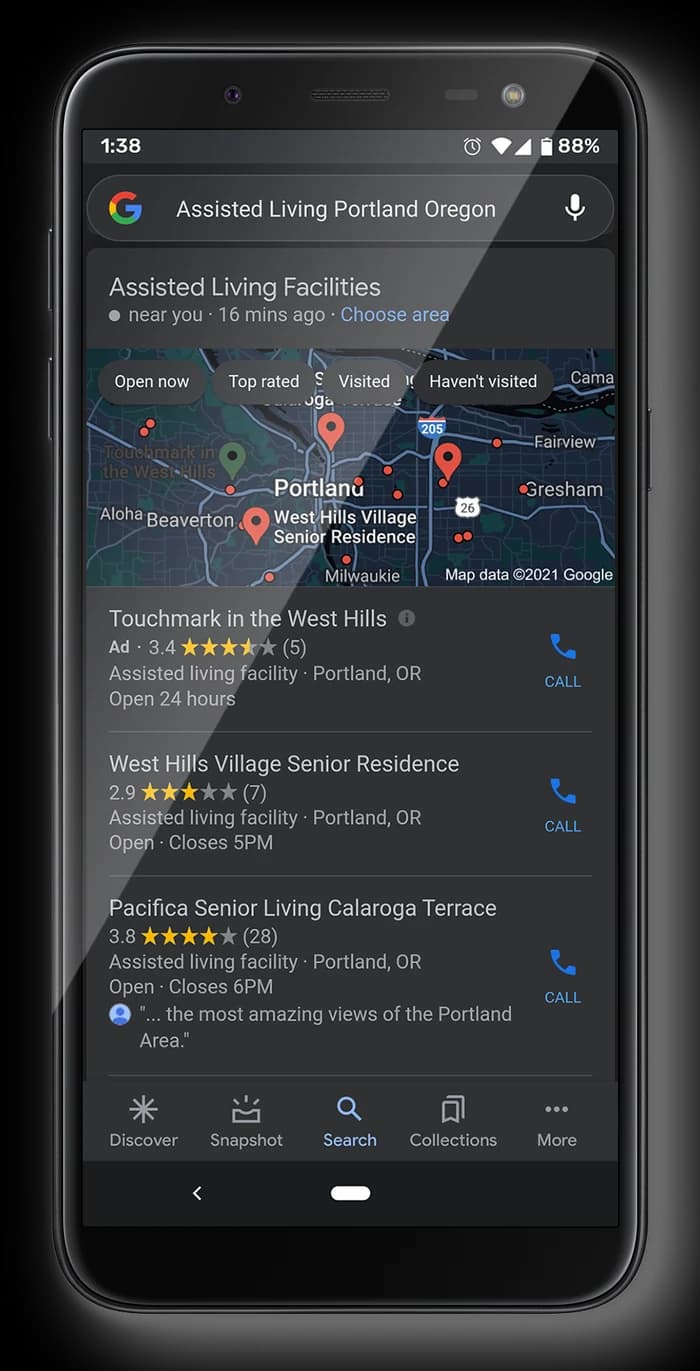
The same logic applies to a hospice competing locally. Proximity searches are settled in the Local Pack above every organic result, and in a live Portland audit we found a national site with a Domain Rating of 55 ranking behind single-location competitors under Domain Rating 2, decided by Google Business Profile strength and citation consistency rather than authority. Being genuinely specific beats being big.
A live local senior care search. The Local Pack takes the whole first screen, before a single organic result.
What we measure, and what we will not do
Admissions and referral source, tracked separately for physician, hospital discharge, facility and direct family search, because the mix tells you which relationship is working and a blended number hides all four. Median length of stay is worth watching alongside it as a quality signal: very short stays usually mean the referral came too late, which is a communication problem upstream rather than a marketing one.
We also track AI mention rate monthly, firing real buying-intent prompts across ChatGPT and Perplexity and recording how often the brand gets named. Given that the four plainest phrases in this category are invisible to the keyword planner, that is one of the only ways to see the layer where these questions are now being asked.
What we will not do here: urgency tactics, scarcity language, retargeting somebody who read the end-of-life page, or anything that treats a family in the worst week of their life as a funnel. That is not a values statement bolted on at the end. It is a constraint we will hold you to, and if a campaign only works with those tactics we will tell you the campaign is wrong rather than quietly running it.
And we will tell you when a number is not real. We came close to sending a client a report showing four months of decline that had not happened, because one data source was reporting against a stale canonical record while three others disagreed. That story is written up here, including the part where we were confidently wrong.
What is the difference between hospice and palliative care?
Palliative care is comfort-focused care that can run alongside treatment intended to cure, at any stage of a serious illness. Hospice is palliative care for someone who is no longer pursuing curative treatment and has a prognosis measured in months. The practical difference for a family is that palliative care does not require giving anything up, which is why it is often the right first conversation and why so many families arrive at hospice later than they needed to.
Does Medicare cover hospice?
Yes, and more completely than any other benefit in senior care. The Medicare hospice benefit covers the care team, medications related to the terminal diagnosis, equipment, supplies and short inpatient respite, typically at little or no cost to the family. That is the opposite of the answer for assisted living, where Medicare covers nothing. About 3,600 US searches a month ask this question at an advertiser competition score of 9, so a clear, accurate answer on your own site is unusually cheap authority to build.
How long can someone be on hospice?
Longer than most families think. Eligibility rests on a physician certifying a prognosis of six months or less if the illness runs its expected course, but that is a certification standard, not a time limit. Patients can be recertified and remain on hospice beyond six months, and some improve and leave hospice entirely. About 1,000 US searches a month ask this at an advertiser competition score of 5. The widespread belief that hospice is a six-month cap is one reason families wait until the last days rather than the last months.
What do families actually search for before they search for hospice?
The symptoms. “Signs of end of life” draws roughly 8,100 US searches a month at an advertiser competition score of 3, which is far more than “when to call hospice” and almost uncontested. That search is somebody awake at 3am watching breathing change and trying to understand what they are seeing. It is the most important page a hospice can write, and it has to be written as care rather than as marketing.
Should a hospice market palliative care separately?
Yes, and it is probably the largest missed opportunity in the category. “Palliative care” draws about 246,000 US searches a month at an advertiser competition score of 21, roughly seven times “hospice near me” at half the competition. Most hospice websites mention palliative in a sentence. It is the earlier, larger, less frightening door into the same organisation, and the families who come through it are not yet in crisis.
How do hospices get more physician referrals?
By making the referral easy to defend. Most hospice census comes from physicians, hospitalists and discharge planners, and a referring clinician is putting their own relationship with the family behind the recommendation. What they need from your site is specific and checkable: response time to a referral, after-hours coverage, which conditions your team handles well, and what the first 48 hours actually look like. Warmth matters to the family; operational specifics are what make a clinician comfortable sending the next one.